Quiz · Hard
Twenty-one applied questions on serotonin syndrome, lithium toxicity, clozapine, EPS, withdrawal, ECT, duty to warn, suicide risk and boundary issues.
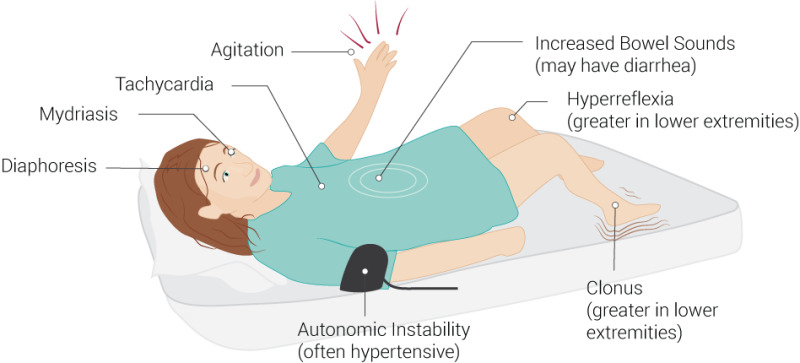
A client taking sertraline and tramadol is brought in with agitation, diaphoresis, tachycardia, diarrhea, dilated pupils and inducible clonus of the ankles. What is the likely diagnosis?
Neuroleptic malignant syndrome
Anticholinergic toxicity
Alcohol withdrawal
Serotonin syndrome
Hyperreflexia, clonus, diarrhea and rapid onset after combining serotonergic drugs suggest serotonin syndrome. NMS has rigidity and a slow onset after an antipsychotic. Image: Beckie Palmer, CC BY 4.0, via Wikimedia Commons.
In this diagram of a synapse, SSRIs act at which labeled structure?
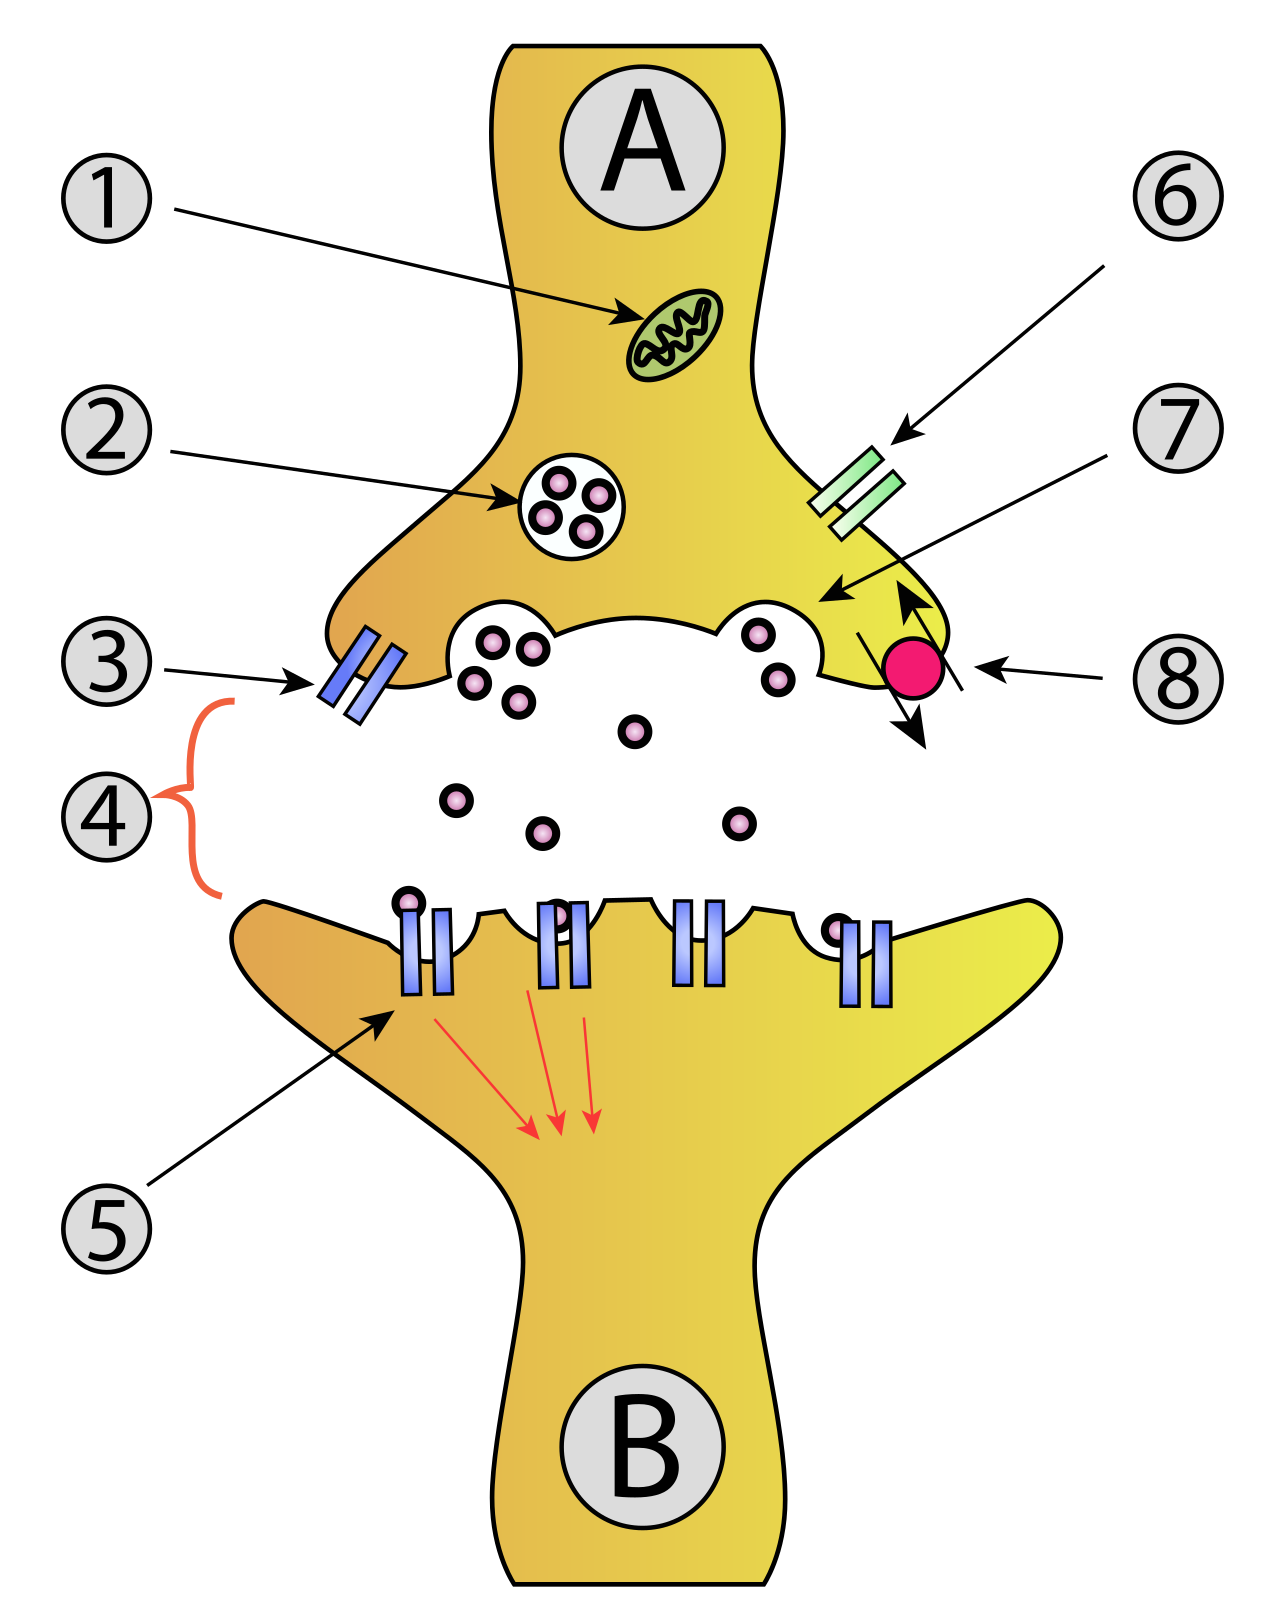
8: the presynaptic reuptake pump
1: the mitochondrion
5: the postsynaptic receptor
6: the calcium channel
SSRIs block the reuptake pump, so serotonin stays longer in the synaptic cleft (4). The mitochondrion supplies energy, the calcium channel triggers vesicle release and the postsynaptic receptor (5) receives the transmitter. Image: Mouagip (vectorization), after Synapse_diag1, CC BY-SA 3.0, via Wikimedia Commons.
A client on a unit has a lithium level of 2.3 mEq/L, with vomiting, ataxia and confusion. What is the priority nursing action?
Hold lithium, notify the provider, and prepare for IV fluids or dialysis
Give the next dose with a snack
Administer a loop diuretic
Encourage fluid restriction
A level above 2.0 mEq/L is moderate-to-severe toxicity. Stop the dose, ensure airway and neurologic safety, give isotonic saline as prescribed, and prepare for hemodialysis if severe.
A client taking clozapine reports a sore throat and fever. Which action is the priority?
Obtain a CBC with absolute neutrophil count and notify the provider
Give acetaminophen and reassess in 24 hours
Teach about throat lozenges
Continue the medication and recheck in a week
Fever and sore throat in a client on clozapine suggest agranulocytosis, a life-threatening complication. An urgent ANC is needed.
A client on haloperidol for three days is restless and unable to sit still, repeatedly pacing the hall. Which condition does the nurse suspect and what is the intervention?
Acute dystonia; give benztropine IV
Akathisia; notify the provider about a dose reduction or propranolol
Tardive dyskinesia; stop the drug
Anxiety; give extra haloperidol
Akathisia is a subjective inner restlessness with pacing. It is often mistaken for agitation, and giving more antipsychotic worsens it.
A client with schizophrenia has been taking an antipsychotic for 3 years and the nurse notices lip smacking and tongue movements. Which action is best?
Perform an AIMS assessment and report the findings to the provider
Give benztropine
Reassure that it is a temporary side effect
Tell the client to stop the medication
These are signs of tardive dyskinesia, which may be irreversible. Document with the Abnormal Involuntary Movement Scale and notify the provider; benztropine can worsen TD.
A client with bulimia nervosa asks about starting an antidepressant. Which medication is contraindicated?
Fluoxetine
Sertraline
Escitalopram
Bupropion
Bupropion lowers the seizure threshold and is contraindicated in eating disorders with purging. Fluoxetine is FDA-approved for bulimia.
A 25-year-old client is admitted after taking an unknown amount of amitriptyline. Which finding is the greatest immediate threat?
Dry mouth
Constipation
Blurred vision
Widened QRS and ventricular arrhythmias on the ECG
Tricyclic overdose causes sodium channel blockade with arrhythmias, hypotension and seizures. Cardiac monitoring and sodium bicarbonate are key. Anticholinergic symptoms are expected but less lethal.
A nurse is caring for a client prior to electroconvulsive therapy. Which action is the priority?
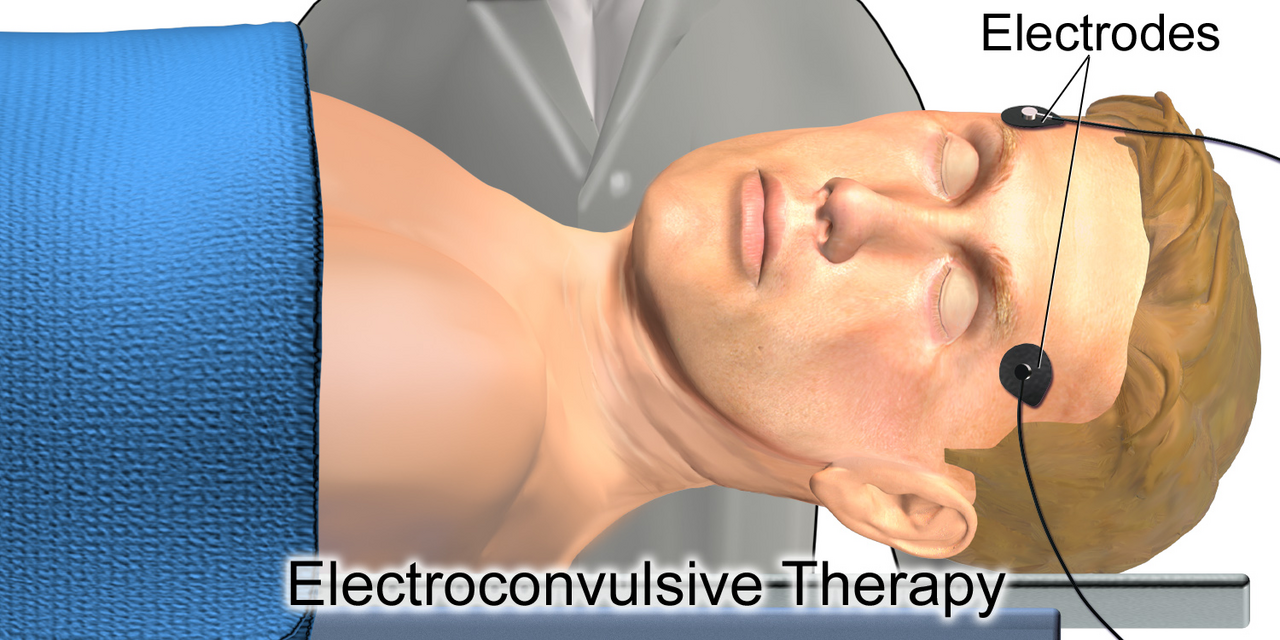
Verify that informed consent is signed and the client has been NPO
Administer the client's morning lithium
Apply restraints to prevent injury
Teach the client to expect no memory changes
Consent and NPO status are required. Lithium is typically held before ECT, restraints are not applied, and temporary memory loss is common. Image: BruceBlaus, CC BY-SA 4.0, via Wikimedia Commons.
After electroconvulsive therapy, the client awakens confused and asks, 'Where am I?' What is the nurse's best action?
Request a CT scan for stroke
Restrain the client to prevent falls
Document the confusion as a permanent deficit
Reorient the client and stay with her until she is alert
Transient confusion is expected after ECT. Reorient, keep the client side-lying with airway protection, and monitor vital signs until alert.
A client threatens, 'I am going to kill my sister when I am discharged.' The nurse should take which action?
Keep the information confidential
Notify the provider and follow the duty to warn procedures
Ask the client to promise not to do it
Wait to see if the client repeats the statement
Credible threats against an identifiable person override confidentiality (Tarasoff). Report to the provider and the proper authorities so the potential victim can be warned.
A client is placed in seclusion for aggression. Which action by the nurse is appropriate?
Check the client every 2 hours
Leave the client in seclusion until the next shift
Observe continuously, check circulation and offer fluids and toileting as per policy
Apply restraints for added safety without an order
Seclusion requires a provider's order and a face-to-face assessment within 1 hour, continuous monitoring, regular checks of needs and release as soon as criteria are met.
A nurse notices a colleague has been spending extra time with a client, giving the client her phone number and bringing in gifts. Which type of behavior is this?
Therapeutic rapport
Boundary violation (a slide toward over-involvement)
Advocacy
Cultural competence
Sharing personal contact information and giving gifts blur the professional boundary. Report the concern to the nurse manager.
Which finding differentiates delirium from dementia in an older adult?
Sudden onset, fluctuating level of consciousness and inattention
Gradual loss of memory over years
Impaired judgment and personality change over months
Stable alertness throughout the day
Delirium is acute and often reversible (infection, medications, hypoxia). Dementia is a gradual, progressive decline with stable alertness until late.
A client with borderline personality disorder tells the nurse, 'You are the only one who understands me; the other nurses are terrible.' What is the best response?
'I'm happy that you like me best.'
'I'm glad you feel comfortable with me. All of the staff work together to provide your care.'
'The other nurses are doing their best, you are being unfair.'
'I will arrange for only me to care for you.'
Splitting pits staff against each other. Respond neutrally, reinforce the team approach, and keep consistent boundaries and communication among staff.
A client with OCD spends 3 hours each morning washing her hands. Which nursing intervention is most appropriate?
Allow time for the ritual while gradually setting limits and teaching exposure and response prevention
Physically stop the client from washing
Tell the client the behavior is silly
Ignore the behavior completely
Stopping the ritual abruptly increases anxiety. Gradually reduce the time with the client's participation, and support SSRIs and exposure and response prevention.
A client is withdrawing from heroin and asks for 'something to help'. The client has yawning, lacrimation, rhinorrhea, piloerection and diarrhea. Which drug does the nurse expect?
Naloxone
Flumazenil
Disulfiram
Clonidine or buprenorphine
These are opioid withdrawal signs. Clonidine reduces autonomic symptoms; buprenorphine or methadone replace opioids. Naloxone would precipitate withdrawal; flumazenil reverses benzodiazepines; disulfiram is for alcohol.
A client taking naltrexone for alcohol use disorder is injured and the provider orders morphine for pain. What should the nurse do?
Administer the morphine as ordered
Double the morphine dose
Give disulfiram first
Question the order because naltrexone blocks opioids
Naltrexone is an opioid antagonist that blocks the effect of morphine. Use a nonopioid analgesic or an alternative approach and notify the provider.
A mother whose child died in an accident says, 'If only I had picked him up myself, this would not have happened.' She is in which stage of grief?
Denial
Acceptance
Anger
Bargaining
'If only' statements reflect bargaining. The nurse listens without argument and supports expression of guilt and grief.
A client who has been depressed tells the nurse, 'I've decided to end it all. I have a gun at home.' Which action is the priority?
Ask the client to sign a no-suicide contract
Leave to find the nurse manager
Encourage the client to talk about the past
Stay with the client, ensure safety and notify the provider; initiate constant observation
A specific plan with access to lethal means is a high-risk emergency. Do not leave the client alone, remove hazards, notify the provider and begin 1:1 observation. A no-suicide contract is not a reliable safety measure.
A client with PTSD becomes terrified and begins shouting during a flashback. Which action is best?
Grab the client and hold her tightly
Tell the client the event is over and she should be over it
Ask the client to describe the trauma in detail
Speak calmly, state the present location and date, and avoid touching the client without warning
Ground the client in the present with a calm voice and orientation cues. Sudden touch may be interpreted as an attack. Detailed trauma discussion is done in therapy, not during acute distress.
