Quiz · Medium
Clinical vignettes on blood gases, sodium and potassium disorders, kidney injury, endocrine disease, liver disease and infection.
Using the table, which disorder fits pH 7.28, PaCO2 28 mmHg, HCO3- 12 mEq/L?
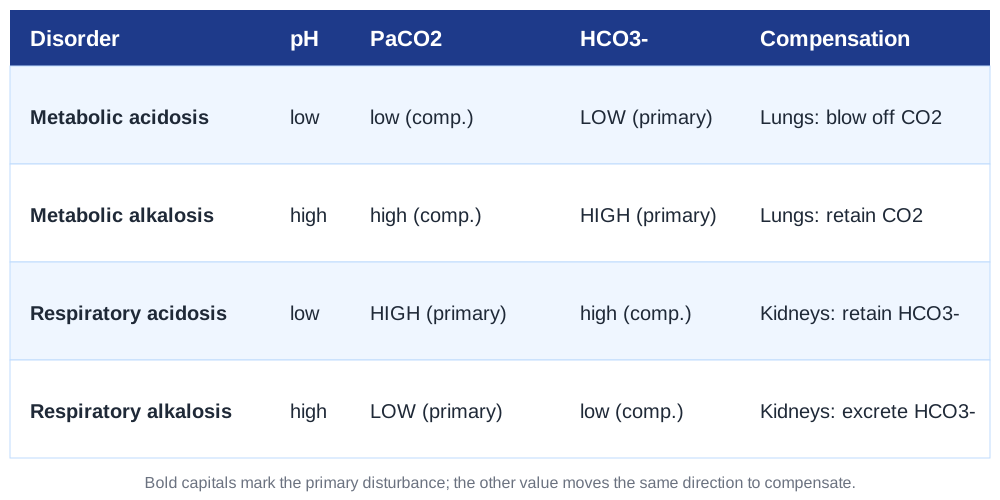
Metabolic acidosis with respiratory compensation
Metabolic alkalosis
Respiratory alkalosis
Respiratory acidosis
Low pH with low HCO3- is a primary metabolic acidosis; the low PaCO2 is compensation. Winter's formula gives 1.5 x 12 + 8 = 26 (plus or minus 2), so compensation is appropriate.
A COPD patient has pH 7.31, PaCO2 62, HCO3- 30. What is the primary disorder?
Metabolic alkalosis
Respiratory acidosis
Metabolic acidosis
Respiratory alkalosis
Low pH with high PaCO2 is respiratory acidosis; the raised bicarbonate is renal compensation.
A patient with vomiting has pH 7.52 and HCO3- 36 mEq/L. Which is most likely?
Metabolic acidosis
Respiratory acidosis
Metabolic alkalosis
Respiratory alkalosis
Loss of gastric acid raises bicarbonate and pH.
Na 140, Cl 100, HCO3- 10. What is the anion gap and what does it suggest?
10; normal gap acidosis
30; non-gap acidosis
12; mixed disorder
30; high anion gap acidosis
140 - (100 + 10) = 30. A gap over 12 suggests MUDPILES causes such as DKA, lactic acidosis or toxins.
Which condition causes a normal anion gap metabolic acidosis?
Severe diarrhea
Methanol ingestion
Lactic acidosis from sepsis
Diabetic ketoacidosis
Bicarbonate loss in stool is replaced by chloride, so the gap stays normal. The others add unmeasured anions.
A 62-year-old has sodium 118 mEq/L, serum osmolality 250, urine osmolality 480, urine sodium 55 and appears euvolemic. What is the most likely diagnosis?
Primary polydipsia
SIADH
Diabetes insipidus
Heart failure
Hypotonic hyponatremia with concentrated urine and high urine sodium in a euvolemic patient is SIADH. Polydipsia gives very dilute urine.
What is the maximum recommended correction of chronic hyponatremia in 24 hours?
No limit if symptomatic
4 mEq/L
8 to 10 mEq/L
20 mEq/L
Faster correction risks osmotic demyelination syndrome. Even symptomatic patients get a limited bolus of hypertonic saline, then slower correction.
First step for a patient with potassium 7.2 mEq/L and peaked T waves?
Oral sodium polystyrene
Hemodialysis
Insulin and glucose
IV calcium gluconate
Calcium stabilizes the cardiac membrane within minutes. Insulin and glucose only shift potassium, and binders and dialysis remove it later.
A diabetic presents with glucose 780, osmolality 340, no ketones, and altered mental status. Which is most likely?
HHS
Alcoholic ketoacidosis
Hypoglycemia
DKA
Severe hyperglycemia with hyperosmolality and no significant ketosis defines HHS.
A man with rheumatoid arthritis has a creatinine rising from 1.0 to 1.5 in 2 days with FENa of 0.5% after severe diarrhea. What is the cause?
Acute tubular necrosis
Prerenal azotemia
Postrenal obstruction
Glomerulonephritis
Low FENa indicates avid sodium retention from hypovolemia. ATN has FENa above 2%.
Which anticoagulant reversal strategy fits a bleeding patient on warfarin with INR 9?
Platelet transfusion
Protamine
Vitamin K plus prothrombin complex concentrate
Idarucizumab
Vitamin K and PCC reverse warfarin. Protamine reverses heparin; idarucizumab reverses dabigatran.
Ascitic fluid PMN count is 480 per mm3 in a cirrhotic with fever and abdominal pain. What is the treatment?
Lactulose
Metronidazole
Large-volume paracentesis only
Ceftriaxone plus albumin
PMN 250 or more defines SBP; third-generation cephalosporin plus albumin lowers renal failure and mortality.
Which serology result indicates immunity from hepatitis B vaccination only?
Anti-HBs positive, anti-HBc negative
IgM anti-HBc positive
HBeAg positive
HBsAg positive
Vaccine contains only surface antigen so core antibody is negative. Anti-HBc appears only after natural infection.
A 28-year-old woman has symmetric polyarthritis, malar rash and proteinuria. Which antibody is most specific?
ANA
Anti-dsDNA
Anti-histone
Rheumatoid factor
ANA is sensitive but not specific. Anti-histone antibodies point to drug-induced lupus.
Needle-shaped, negatively birefringent crystals are seen in the joint fluid of?
Osteoarthritis
Pseudogout
Gout
Septic arthritis
Uric acid crystals are needle-shaped and negatively birefringent; pseudogout crystals are rhomboid and positively birefringent.
A patient has high TSH and low free T4. Which is correct?
Secondary hypothyroidism
Subacute thyroiditis
Graves disease
Primary hypothyroidism
Pituitary reads low T4 and raises TSH. Secondary hypothyroidism has low or inappropriately normal TSH.
Hyperpigmentation, hyponatremia, hyperkalemia and hypotension. What is the diagnosis?
Primary adrenal insufficiency
Hyperaldosteronism
Pheochromocytoma
Cushing syndrome
High ACTH drives pigmentation and aldosterone deficiency causes salt wasting and hyperkalemia. Secondary adrenal insufficiency lacks both.
True or false: in a patient with diabetic ketoacidosis and potassium 2.8 mEq/L, insulin should be started immediately.
True
False
False. Insulin drives potassium into cells and can precipitate fatal arrhythmias. Replace potassium first until K+ is 3.3 or above.
Which empiric therapy is appropriate for a patient with neutropenic fever?
Oral amoxicillin
Cefepime within 1 hour
Wait for cultures
Vancomycin alone
Febrile neutropenia is an emergency; start an anti-pseudomonal beta-lactam immediately.
